


Abstract
Introduction Artificial intelligence (AI) and machine learning are increasingly used in dermatology, primarily for diagnosing skin cancer and classifying disease severity. Primary care providers (PCPs) and emergency physicians have higher error rates in diagnosing dermatologic conditions compared to dermatologists. This study evaluates the performance of an AI-driven dermatologic image analytics tool in identifying common skin disorders from classical images used in medical education.
Methods This prospective study analyzed 42 classical images of common skin disorders using the bellePro application (version 2.1.0; BelleTorus Corporation), trained on over 400,000 dermatologic images. A set of dermatologic images used in a national board review course underwent blinding and independent validation by an academic dermatology department. This module provides AI-powered predictions from cell phone photos, ranking them by “image match scores” (higher values indicate better predictions). The primary outcome was the accuracy of three image predictions in identifying known diagnoses, along with the corresponding image match scores.
Results The AI tool correctly predicted 38 out of 42 skin disorders (positive predictive value was 90.5%) as the top differential on the first attempt for all three attempts. Four conditions (angioedema, squamous cell carcinoma, hand foot and mouth disease, and chickenpox) were included in the prediction differential list each attempt but never ranked first, bringing the total to 42/42 (100%). None of the correctly identified disorders had an average image match score below 0.64. The average image match score for correct diagnoses was 0.896 (SD = 0.098).
Conclusions The findings suggest that this AI-based dermatologic image analytics tool performs effectively on classical images of common skin disorders typically seen in clinical practice. This has potential to serve as an adjunct for providers to improve patient outcomes in environments lacking timely access to dermatology resources.
- Artificial Intelligence
- Deep Learning
- Dermatology
- Emergency Medicine
- Machine Learning
- Medical Errors
- Primary Health Care
- Prospective Studies
- Skin Cancer
Introduction
Dermatologic conditions can present significant diagnostic challenges in clinical practice. Misdiagnosis or delayed diagnosis of dermatologic conditions can lead to prolonged suffering for patients and unnecessary strain on healthcare resources.
With rapid advancements in artificial intelligence (AI) technologies, there is growing interest in utilizing AI for various medical applications, including dermatology. AI algorithms, particularly those based on deep learning techniques, have demonstrated remarkable capabilities in image recognition and pattern analysis, making them promising tools for assisting healthcare professionals in diagnosing dermatologic diseases.1–4 Deep learning is a subset of machine learning that utilizes multiple layers of “neural networks,” modeled after the human brain, to automatically recognize and learn different features specific to a dataset.1–3 Much of the current research work regarding AI in dermatology has focused on the diagnosis of skin cancers and disease severity classifications.5–7
This study explores the potential of AI in improving the diagnosis and management of dermatologic diseases in clinical practice. By leveraging AI technologies, clinicians can augment their diagnostic skills, improve patient outcomes, shorten diagnosis time, and optimize resource utilization.8
In this study the performance of a dermatologic AI tool in diagnosing common skin disorders from a national board review course was evaluated. This manuscript will delve into the current landscape of AI applications in dermatology, examining the strengths and limitations of existing AI models for diagnosing skin conditions. Additionally, we will discuss the unique challenges and opportunities associated with implementing AI-driven dermatologic diagnosis systems in clinical practice.
Methods
In this prospective study, a set of classical images of common skin disorders used for teaching dermatology in a national board preparation course were evaluated. These images underwent blind, independent confirmation by the chairman of the Academic Department of Dermatology. These images were evaluated using the bellePro application (version 2.1.0; BelleTorus Corporation), loaded on to an iPhone16. There were three separate images taken of each condition. After the pictures were obtained, each were cropped to remove extraneous information, in a manner similar to how this is used in a clinical setting. This application has been trained on over 400,000 dermatologic images. This application does not utilize or store clinical information other than that obtained from the image. This module provides artificial intelligence–powered predictions, ranking them based on the image match scores between 0 and 1, where higher values indicate better predictions. The primary outcomes were how often the correct diagnosis was obtained, highest image-match-score ranking, on the first image attempt or on subsequent attempts.
This image match score reflects a mathematical sigmoid value of an image’s similarity to those in the database. A higher score (near 1) suggests that the image has many similar geometric features to a known skin condition in the database. In contrast, a low score (near 0), suggests that the image is not similar to the images in the database. This image match score (y-axis) is based on the mathematical S-shaped sigmoid curve with the x-axis representing the number of geometric or colorimetric characteristics that match with the diagnosis. Matching characteristics were represented by positive values, while non-matching characteristics were represented by negative values. Many sigmoid functions, including the logistic function, are used in these artificial neural networks.
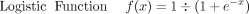
A sigmoid function has a first derivative that is bell-shaped. Conversely, the integral of any continuous, non-negative, bell-shaped function (with one local maximum and no local minimum, unless degenerate) is sigmoidal (Figure 1), as are the reported image match scores. The dermatologic predictions are better with optimal lighting, proper cropping, and minimal distractions/distortions in the images. The accuracy of three image predictions in identifying known diagnoses, along with the corresponding image match scores were the primary outcomes. Descriptive statistics were reported along with the mean and standard deviation of the image match scores for correct identification of the dermatologic conditions.

Dermatologic AI programs use a variety of geometric features to identify skin lesions. These features help the AI analyze the shape, size, and structure of lesions, aiding diagnosis of these conditions and differentiating between benign and malignant lesions. Some common geometric features include:
Border Irregularity: AI examines the outline of the lesion for uneven, scalloped, or poorly defined edges, which can indicate malignancy.
Asymmetry: Lesions that are asymmetrical (ie, one half does not match the other half in shape) are more likely to be malignant, while symmetrical lesions tend to be benign. AI measures asymmetry to help identify such cases.
Diameter: The size of the lesion is measured. Lesions larger than a certain size (often around 6 mm) are more likely to be cancerous.
Color Variation: Although this is more of a colorimetric feature, the distribution of colors within the lesion can create patterns that are analyzed geometrically. Multiple colors or uneven distribution can be a sign of malignancy.
Shape Features: AI analyzes the overall shape of the lesion (eg, circular, oval, irregular). Irregular shapes are more often associated with malignancy.
Area and Perimeter Ratio: The ratio of the area of the lesion to its perimeter provides insights into the lesion’s nature. A high perimeter-to-area ratio might suggest an irregular shape.
Compactness: This feature describes how tightly packed the lesion is in terms of its area and perimeter. Higher compactness values often correlate with more regular, benign lesions.
These geometric features are typically used alongside other attributes, such as texture and color, to provide a comprehensive analysis. AI systems trained with large datasets can use these features to improve diagnostic accuracy, supporting medical practitioners in clinical decision-making. Utilization of images in this study does not require IRB review as this is secondary analysis of de-identified data, which the IRB has previously determined to be “not human subjects research.”
Results
A total of 42 common skin disorders seen in clinical practice were evaluated using this dermatologic AI tool. Out of these samples, 38 (positive predictive value was 90.5%) were correctly diagnosed as the top differential on all three attempts. Four additional disorders—specifically, angioedema, squamous cell carcinoma, hand-foot-and-mouth disease, and chickenpox—were consistently included in the differential but never as the highest-ranked diagnosis, resulting in a total identification rate of 42/42 (100%). Among correctly identified disorders, none had an average image match score below 0.64 (Figure 2). The mean image match score for correct diagnoses was 0.896 (SD = 0.098).

Discussion
This prospective study demonstrated that AI applications have the capability to accurately identify skin pathologies. The AI bellePro application correctly identified 90.5% of common skin disorders on the first image attempt, with an average image match score of 0.896. The results are comparable to those of other studies that have assessed the utility of AI-assisted diagnosis in dermatology-related pathologies.5–7 This AI-based dermatologic image analysis tool performed slightly better than our review of these images with an older version.
A study by Sboner et al9 demonstrated that the performance of multiple classifiers (ie, algorithms in conjunction) was comparable to that of eight dermatologists in diagnosing melanoma from digital images. In their study, dermatologists more accurately diagnosed melanomas than single-classifier systems; however, for multiple classifier systems, the performance was comparable between groups. Several studies in the literature have found that AI image classification can match or even exceed dermatologists’ performance in diagnosing melanoma using dermoscopy.6,10 This study had similar findings, showing the reliability of AI in accurately diagnosing skin conditions, indicating that AI may be a reliable diagnostic tool in dermatology.
This study further expands current findings by assessing several other common skin pathologies in addition to melanoma. A study by Esteva et al11 in 2017 showed that deep learning algorithms achieved high diagnostic accuracy for melanoma and other skin cancers, supporting the findings of high image match scores for melanoma and basal cell carcinoma (BCC), which were 0.93 and 0.97, respectively.
Given the acute and severe nature of conditions such as angioedema, meningococcemia, pemphigus, and bullous pemphigoid, a considerable proportion of these cases are likely to present emergently for initial evaluation and management to a clinical setting. The dermatologic AI application had difficulty diagnosing angioedema, highlighting the complexity of the condition. Diagnosing angioedema requires a multifaceted clinical evaluation, including assessing vital signs, obtaining a detailed history, and performing a thorough physical examination to identify potential triggers and evaluate the extent of airway involvement.12,13 This complexity likely contributes to the lower performance of the AI application in this area. The differential for angioedema of the tongue included hypothyroidism, acromegaly, and macroglossia, which may be difficult to differentiate based on an individual image. In addition, squamous cell carcinomas (SCCs) often appear very similar to keratoacanthomas to the practicing dermatologist and to dermatological AI programs. In contrast, the AI application demonstrated high accuracy in diagnosing conditions like meningococcemia and herpes simplex, both characterized by distinct clinical features. For instance, meningococcemia can be identified by specific clinical variables such as characteristic skin hemorrhages, universal distribution, and poor general condition, as noted by Nielsen et al.14 These clear markers help the platform perform with higher accuracy. Similarly, the program accurately diagnosed psoriasis and BCC, both with high image match scores, emphasizing its strength in identifying conditions with well-defined dermatologic presentations.
A substantial number of dermatology-related emergency department visits are for non-urgent or semi-urgent skin problems, suggesting that patients may present to the emergency department due to difficulties accessing other clinicians.15,16 A study evaluating emergency department (ED) utilization for dermatologic conditions from 2009-2015 found that skin problems comprised 6.4% of total pediatric ED visits.17 AI software appears to be a helpful adjunct for evaluating patients in primary care or emergency settings.
Implementing AI in clinical practice does not come without challenges. Ethical and legal concerns, including patient confidentiality and professional liability, must be considered. Clinicians need to be prepared to interpret AI-generated results within the context of patient-specific clinical scenarios while ensuring robust patient information safeguards, as there is a risk of relying too heavily on initial AI-generated diagnoses. In the former scenario, anchoring bias has been shown to reduce clinician diagnostic accuracy by 11.3% compared to baseline.18 Additionally, AI systems are not immune to anchoring bias, where disproportionate weight is given to initial data points such as presenting symptoms or early test results, failing to adequately adjust diagnostic likelihoods in light of new information. These challenges must be carefully considered when implementing systematic changes.
Primary care providers (PCPs) and emergency clinicians often encounter dermatologic conditions, but their accuracy in diagnosing these conditions can vary significantly. Studies suggest that PCPs and emergency clinicians correctly diagnose dermatologic conditions around 50%–70% of the time.19–21 While PCPs can accurately diagnose common and straightforward skin conditions, their diagnostic accuracy tends to be lower for less common or more complex dermatologic issues. Wilmer19 found that dermatologists correctly diagnosed skin conditions about 92% of the time, compared to 52% for non-dermatologists.
Limitations
Dermatologic AI systems are susceptible to confounding factors related to image quality, brightness contrast, blurry photos, skin markings, hair, background skin diseases, and peculiar anatomic sites. In addition, many AI algorithms are mainly trained on datasets of Caucasian patients, limiting the representation of variability and disease presentation. Some have suggested that the confounding of lesion-adjacent artifacts could be overcome with the process of image segmentation, which separates the lesion from the background information. Older versions of this diagnostic tool may not perform as well as the newer versions that are based off of larger datasets and newer algorithms.
This study evaluated classic teaching images, which may be much easier to diagnose than typical skin lesions seen in clinical practice. One can assume that the accuracy of this dermatologic AI image analytics tool, which has moderate accuracy on a data set of 400,000 dermatologic images, would only be improved on a future dataset of 40 million images. The addition of pertinent clinical information could also improve the accuracy of these dermatologic analytic tools.
Conclusion
Patients frequently present in clinical practice for skin concerns due to the inability to see a dermatologist in a timely manner. AI is a rapidly evolving force in the landscape of medicine. The primary care office and ED are ideal environments for implementing AI-assisted dermatologic analytic tools that can serve as an adjunct to improve the diagnostic accuracy of dermatologic conditions by clinicians in many types of practices.
Conflicts of Interest
None.
Author Contributions
DVJ was involved in the conception and methodology design. DVJ, MMT, and KKP were involved in the conduct of the study, acquisition of data, and the analysis and interpretation of the results. DVJ, MKB, KKP, and BAS wrote the first draft of the manuscript, and all authors edited, reviewed, and approved the final version of the manuscript. DVJ is the guarantor of this work and, as such, had full access to all the data in the study, and takes responsibility for the integrity of the data and the accuracy of the data analysis.
Corresponding Author
Dietrich von Kuenssberg Jehle, MD, Department of Emergency Medicine, The University of Texas Medical Branch, Galveston, TX, dijehle{at}utmb.edu
This article was externally peer reviewed.
- Received for publication July 8, 2025.
- Accepted for publication October 27, 2025.
References



Jump to section
Related Articles
Cited By...
- No citing articles found.